


Presentation
Hereditary spastic paraparesis (HSP) is characterised by the onset, in children or adults, of motor impairment (spasticity, pyramidal syndrome, weakness) and deep sensory impairment in the lower limbs.
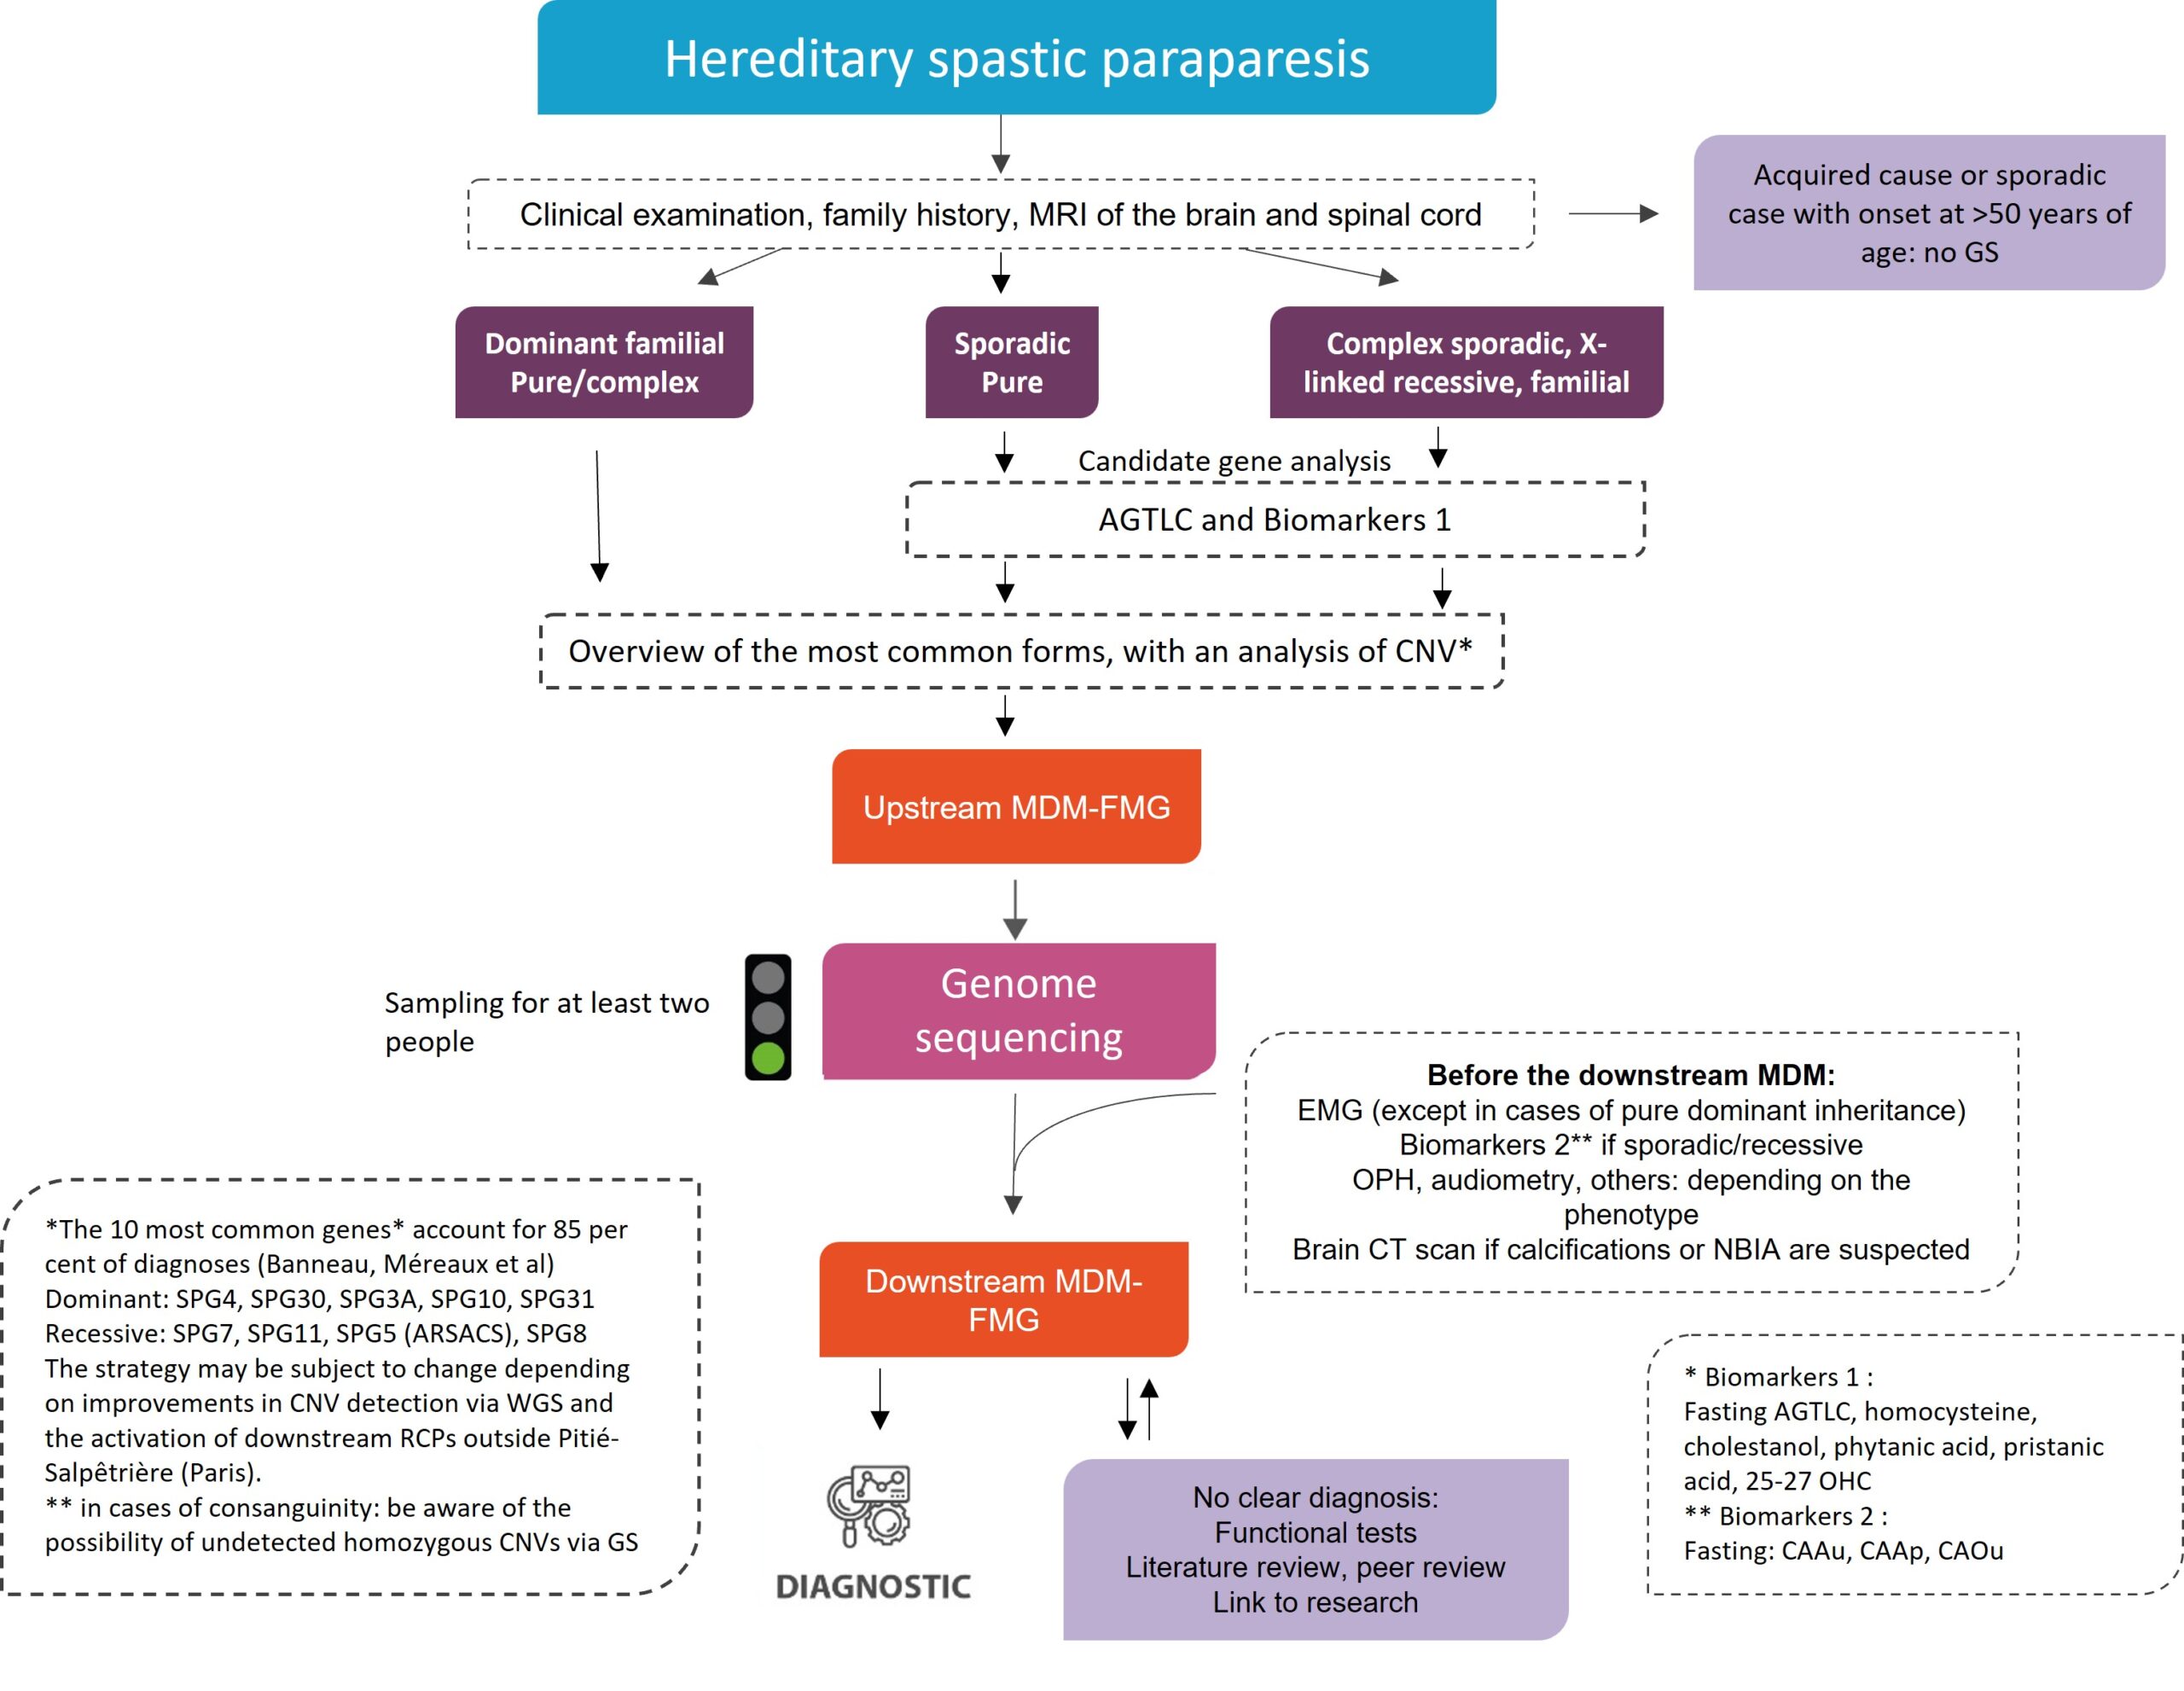
There is one major gene: SPG4 (approximately 15-20% of sporadic forms, 40% of dominant forms), followed by other relatively common genes (dominant: SPG30, SPG3A, SPG10, SPG31; recessive SPG7, SPG11, SPG5, SACS, SPG8, SPG30). CNVs are a common mutational mechanism in PSH (10-25% of SPG4 mutations) and are currently not well detected in very high-throughput sequencing (STHD)1.
Beyond SPG4 (and the most common genes), the molecular bases of PSH are numerous and heterogeneous, still poorly understood, with more than 100 genes involved to date, leading to overlaps with other syndromic categories (ataxias, leukodystrophies, Parkinson’s syndromes, NBIA, neuropathies, etc.) and for which Genome Sequecing is of real interest.
These 10 most common genes account for 85% of diagnoses (Banneau, Méreaux et al). The strategy is likely to be modified as CNV detection in GS improves and all downstream MDMs are activated.
Criteria before considering a discussion in MDM-FMG
No GS proposed at present for:
- Sporadic cases, onset > 50 years of age
Sporadic cases with onset < 50 years of age or familial cases:
- Complete clinical examination
- Brain MRI with T2*/SWI and sagittal T1 sequences, to be supplemented with a brain CT scan if there is any doubt about iron/calcium deposits
- Spinal MRI
- Unless clearly dominant familial form:
- Biomarkers 1: fasting AGTLC, homocysteine, cholestanol, phytanic acid, pristanic acid, 25-27 hydroxycholesterol
- Panel of the most common genes with CNV analysis1
(!) If ataxia is associated, consider expanding pathologies (SCA for dominant forms, Friedreich for recessive forms)
Send in pairs at a minimum, in trios if possible
- Collect ≥ 1 other affected individual (all available, preferably distant relatives) and/or
- Collect ≥ 1 healthy parent:
- Sporadic case: both parents if possible
- Healthy relative (first cousin, etc.): preferably from the ‘non-at-risk’ branch;
- Healthy but at-risk relatives: prioritise those older than the age at which the disease first appeared in the index case
(!) Incomplete penetrance and variable expressivity of diseases; beware of unwanted presymptomatic diagnosis
• ‘Solo’ sampling authorised in exceptional cases: if disease onset <20 years of age or clear family context (≥2 affected individuals, consanguinity)
Genome Sequencing in diagnostic strategy
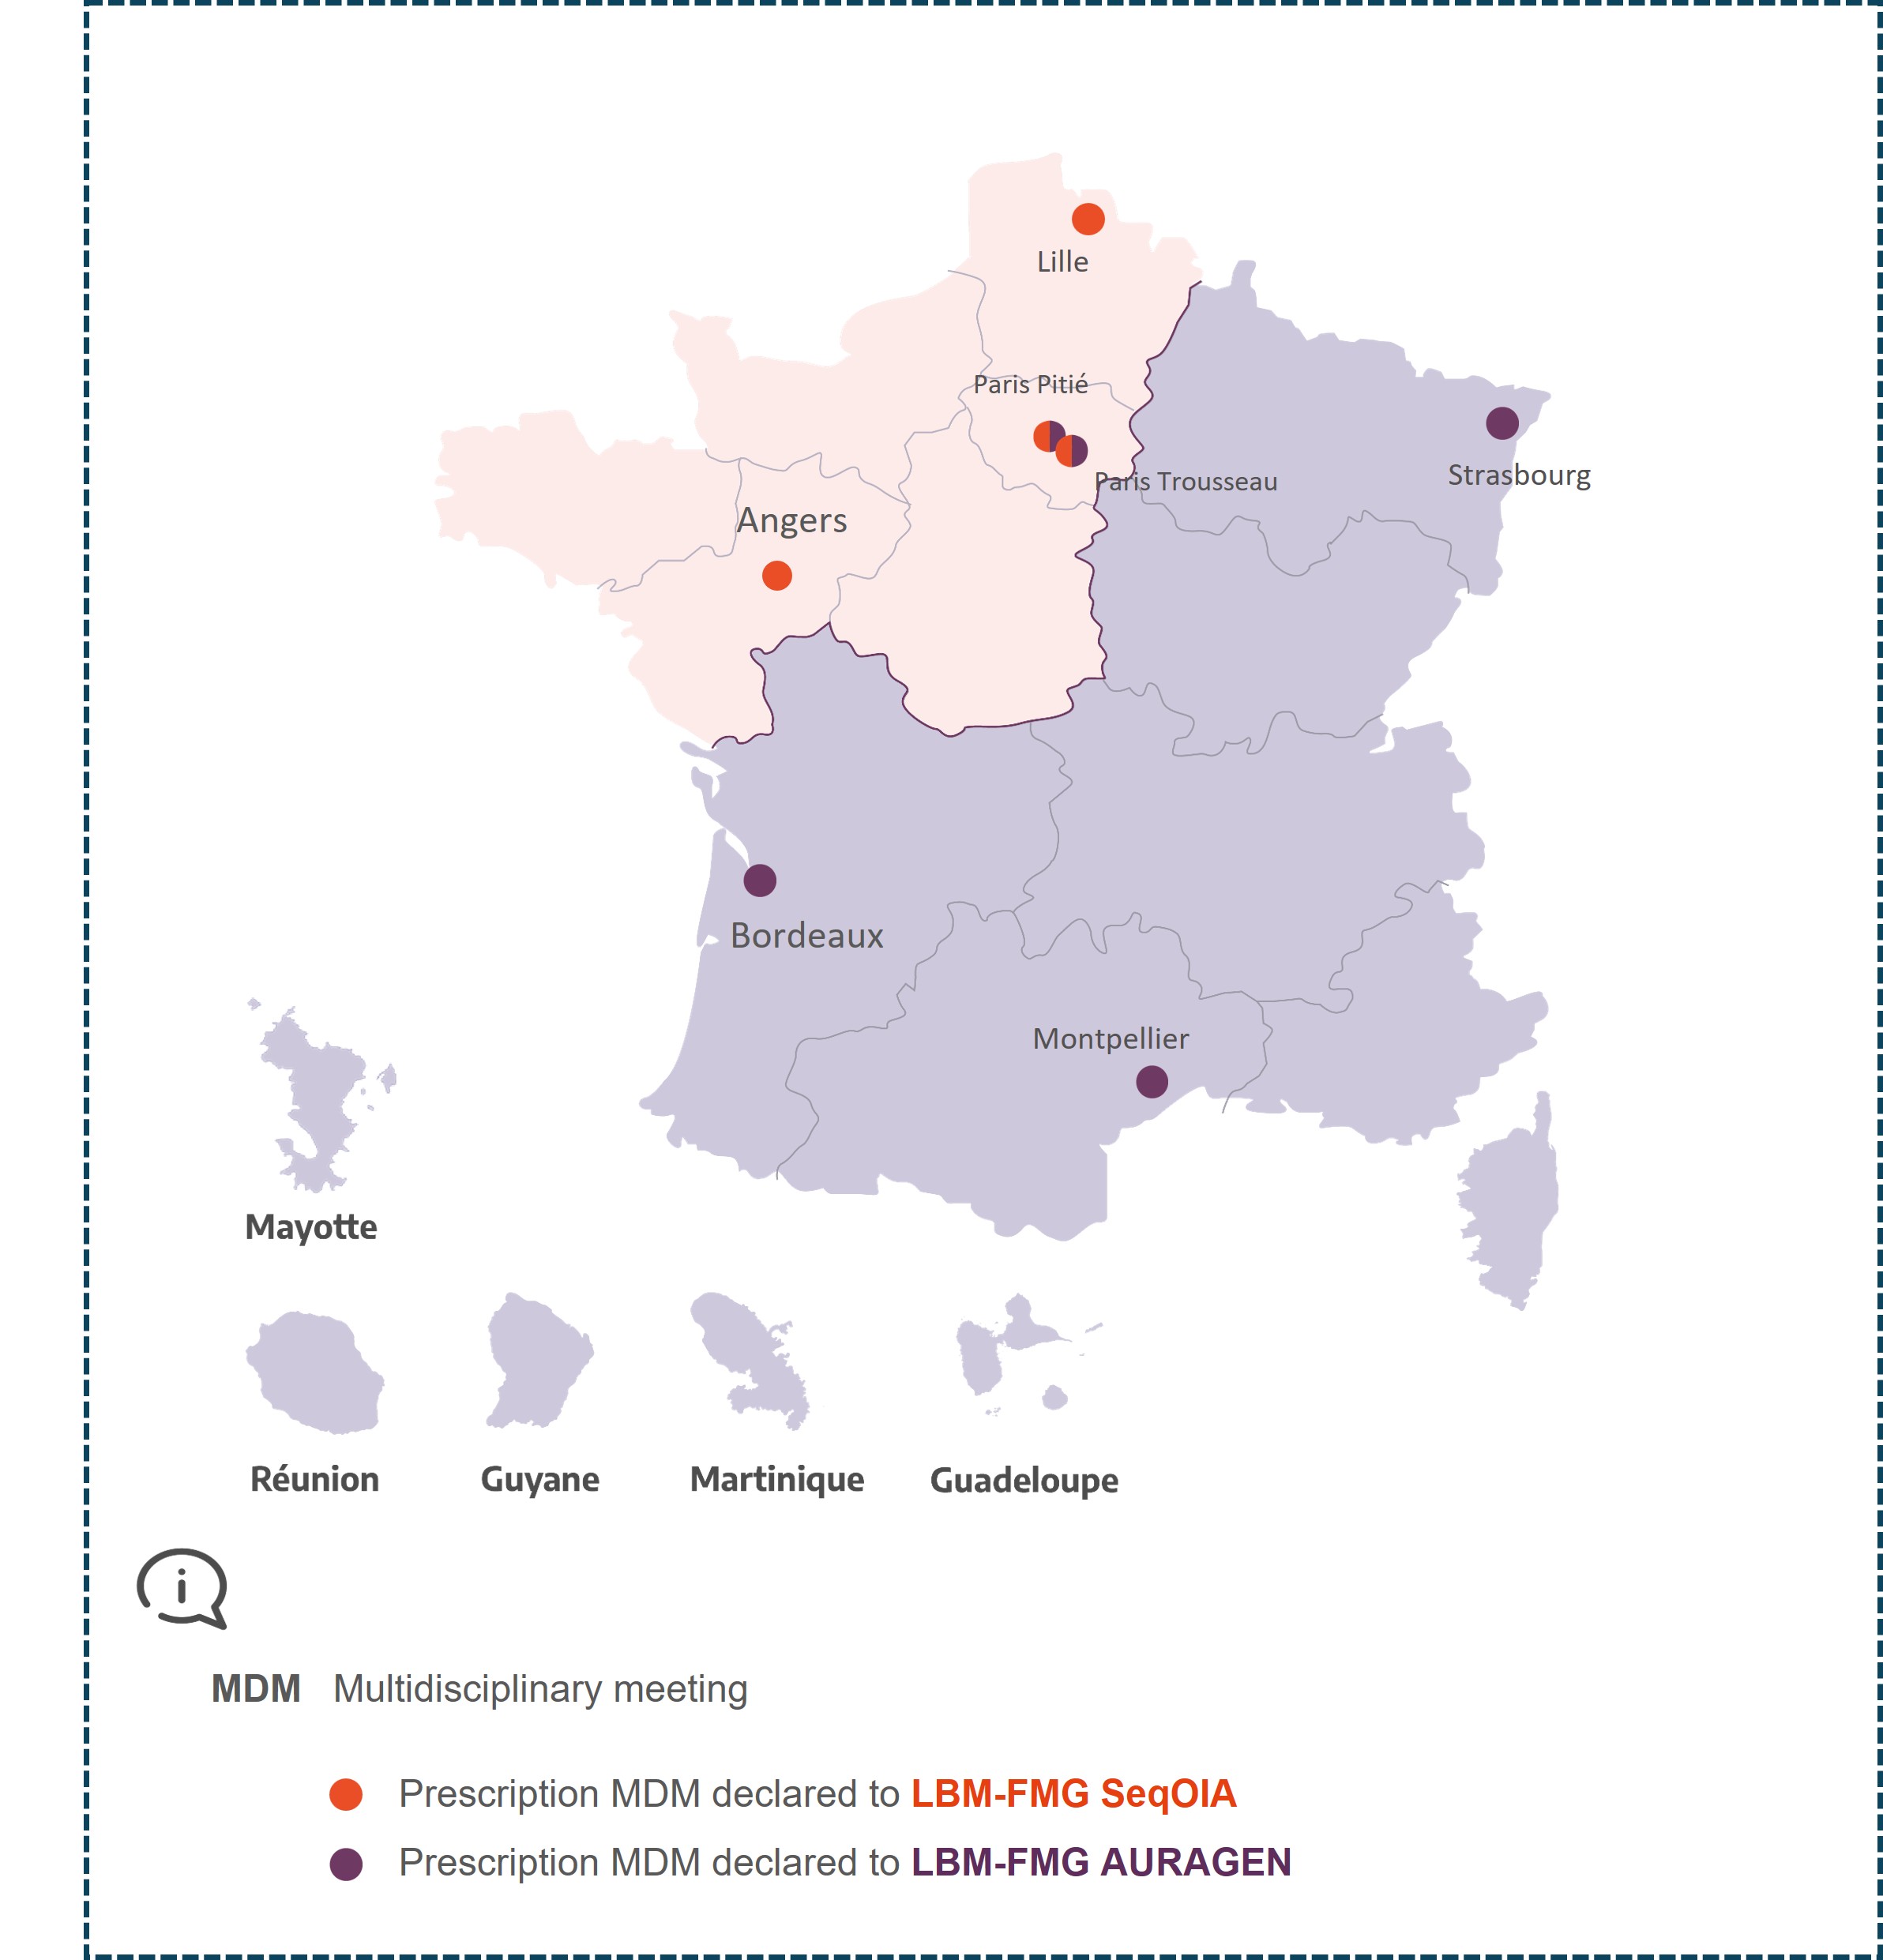
MDM cartography
MDM Neurogenetics Paris Pitié
Claire EWENCZYK
Alexandra DURR
Perrine CHARLES
Anna HEINZMANN
MDM Neurogenetics Paris Trousseau
MDM Neurogenetics Angers
MDM Neurogenetics Bordeaux
Cyril GOIZET
MDM Neurogenetics Strasbourg
Mathieu ANHEIM
mathieu.anheim@chru-strasbourg.fr
Christine TRANCHANT
christine.tranchant@chru-strasbourg.fr
Solène FRISMAND
Matthieu BEREAU
Christel THAUVIN
Anne DOE DE MAINDREVILLE
adoedemaindreville@chu-reims.fr
Juliette PIARD
MDM Neurogenetics Montpellier
MDM Neurogenetics Lille
David DEVOS
Luc DEFEBVRE
Sylvie NGUYEN-THETICH
sylvie.nguyenthetich@chru-lille.fr
Gaël NICOLAS
Eugénie MUTEZ