


Presentation
Many rare respiratory diseases remain unexplained by targeted gene panel analysis. Thus, a genetic cause is identified in nearly 90% of cases of central hypoventilation (CH), 80% of primary ciliary dyskinesia (PCD), 30% of diffuse interstitial lung disease (ILD), 25% of sporadic forms of venous occlusive disease in young people, 15% of isolated forms of pulmonary arterial hypertension (PAH), and less than 10% of syndromic pulmonary development abnormalities (SPD) or idiopathic bronchiectasis (IBE). Unexplained forms may benefit from Genome Sequencing.
Criteria before considering a discussion in MDM-FMG
Criteria for pulmonary arterial hypertension (PAH) or pulmonary veno-occlusive disease (PVOD)
- Pulmonary arterial hypertension (PAH) or pulmonary veno-occlusive disease (PVOD) in children or young adults not associated with pathologies explaining these diseases. Samples from parents should ideally be available for trio STHD analysis.
- Familial PAH or PVOD (at least 2 cases up to the 3rd degree). Samples from at least 2 affected patients must be available for STHD analysis.
- Negative genetic panel analysis.
Criteria for diffuse interstitial lung disease (ILD)
- Diffuse interstitial lung disease (ILD) in children with no known aetiology. Samples from parents should ideally be available for trio STHD analysis.
- Familial ILD (at least 2 cases up to the 3rd degree). Samples from at least 2 affected patients must be available for STHD analysis.
- Pulmonary or extrapulmonary phenotype suggesting a genetic cause (e.g. suspected telomeropathy with DIP and familial or sporadic haematological or hepatic involvement). Samples from at least 2 relatives must be available for STHD analysis
- AND negative targeted genetic panel analysis
Criteria for primary ciliary dyskinesia (PCD)
- Negative study of PCD-related genes (NGS panel and/or exome) in a patient with respiratory signs suggestive of PCD with nasal NO <diagnostic threshold on two occasions with at least one of the following:
- Situs inversus
- Ciliary ultrastructure abnormalities typical of PCD in EM
- Moderate clinical suspicion of PCD but personal or familial (siblings) extrarespiratory clinical manifestations suggestive of ciliopathies (retinitis pigmentosa, congenital heart disease, hydrocephalus, polysplenia, morphological abnormalities of the sperm flagellum, etc.)
Criteria for central hypoventilation (CH)
- Central hypoventilation (= persistent alveolar hypoventilation not explained by neurological, neuromuscular or pulmonary parenchymal involvement). Samples from parents must be available for GS analysis in trios.
- Familial central hypoventilation (at least 2 cases up to the 3rd degree). Samples from at least 2 affected patients must be available for GS analysis.
- Negative genetic analysis of the PHOX 2B gene.
Criteria for abnormal pulmonary development (APD)
- Abnormal pulmonary development in children with pulmonary or extrapulmonary phenotype suggesting a genetic cause (at least 1 criterion):
- Syndromic malformation
- Clinical severity that may warrant genetic counselling for future pregnancies
- Documented risk of recurrence
- Familial pulmonary development anomaly in children (at least 2 cases up to the 3rd degree). Samples from at least 2 affected patients must be available for GS analysis
- AND negative genetic panel analysis for known genes
Criteria for idiopathic bronchiectasis (IBE)
- Idiopathic bronchiectasis in children with a phenotype suggesting a genetic cause (at least 1 criterion):
- Syndromic malformation
- Clinical severity that may justify genetic counselling for future pregnancies
- Documented risk of recurrence
- Familial idiopathic bronchiectasis (at least 2 cases up to the 3rd degree). Samples from at least 2 affected patients must be available for GS analysis
- AND negative genetic panel analysis for known genes
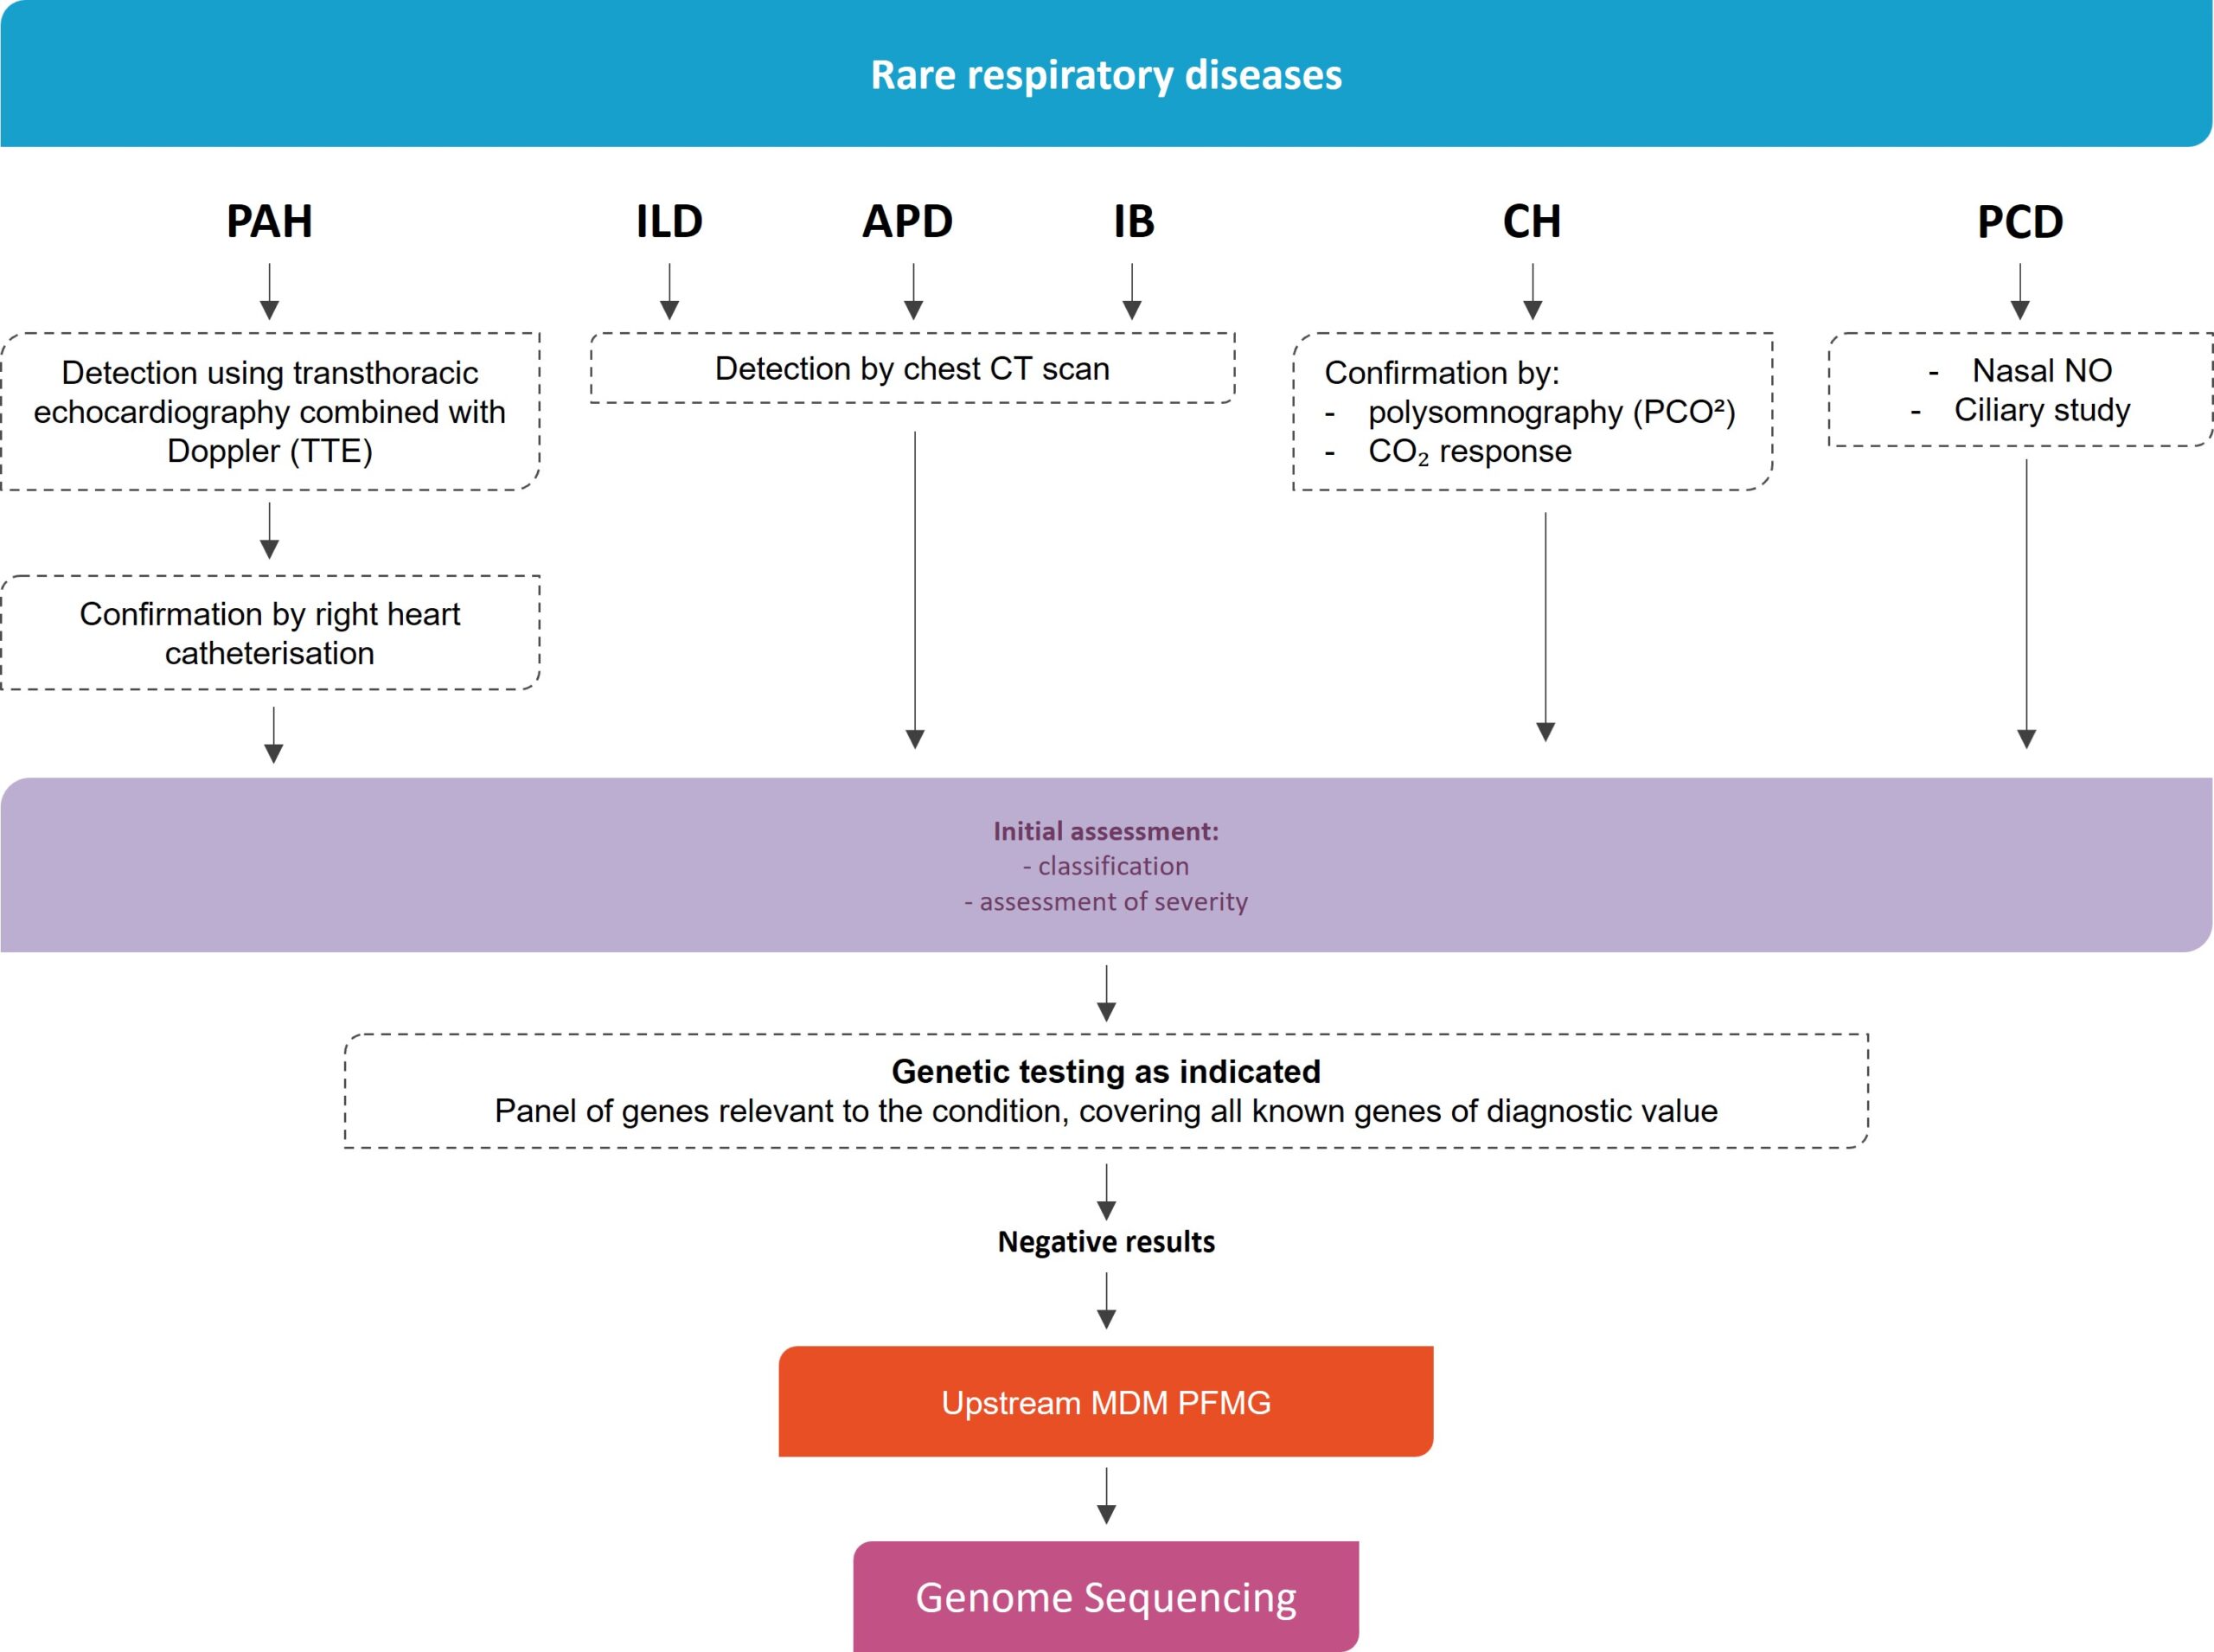
Genome Sequencing in diagnostic strategy
MDM cartography
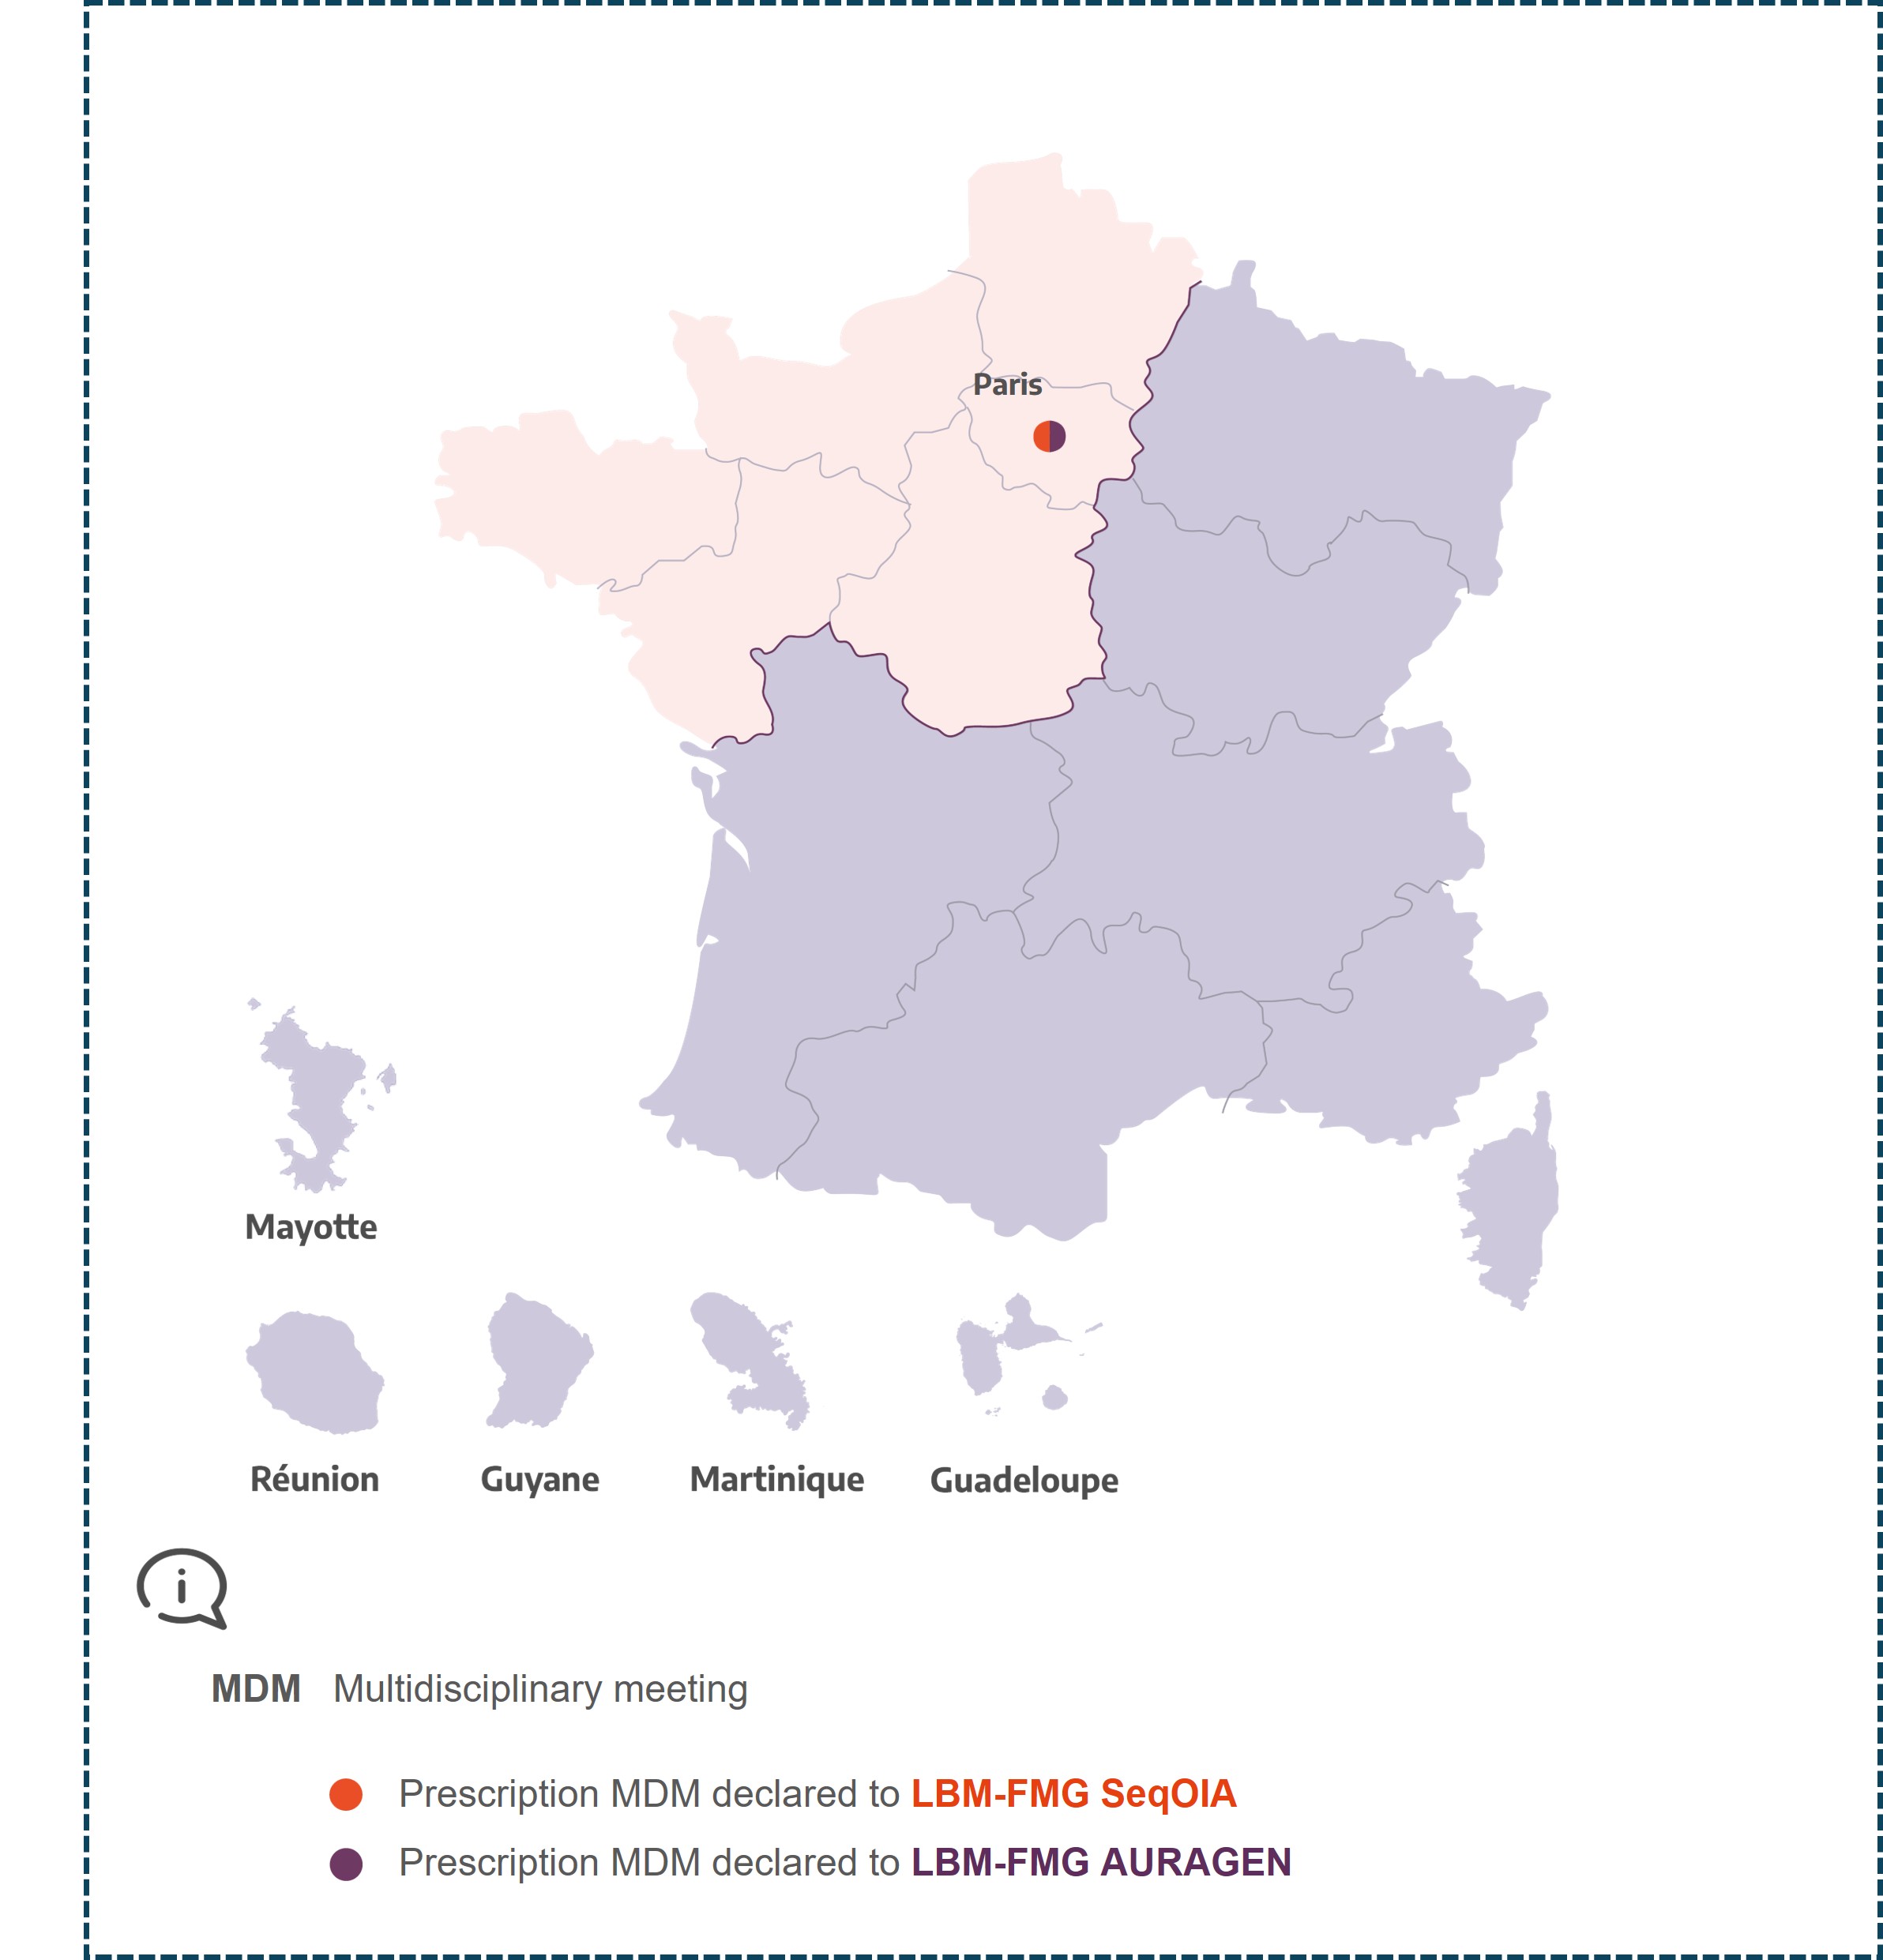
MDM-FMG Rare respiratory diseases
PAH
David Montani
ILD
Raphael Borie
Nadia Nathan
Vincent Cottin
Philippe Reix
PCD
Bernard Maitre
Guillaume Thouvenin
CH
Maxime PATOUT
Benjamin DUDOIGNON
APD
Christophe Delacourt
Alice Hadchouel
alice.hadchouel-duverge@aphp.fr
Idiopathic bronchiectasis (non CF non PCD)
Ralph Epaud
Véronique Houdouin